Immunize.org supports evidence-based vaccination recommendations and schedules. Read more at About Us.

Ask the Experts: All Questions

Ask the Experts is one of our most popular destinations for healthcare professionals. Our experts provide clear, easy-to-understand answers to commonly asked questions about vaccines and their use.

How to Find Your Answer

  • Some filter options may become disabled as you narrow your selections.
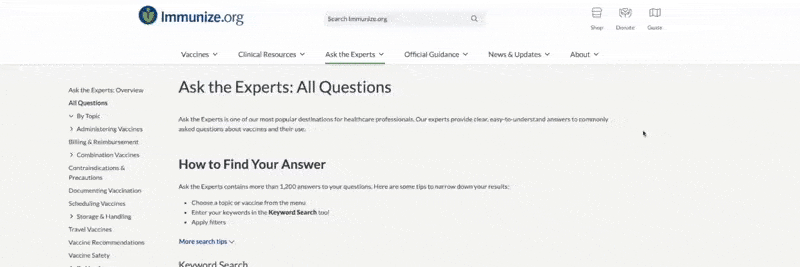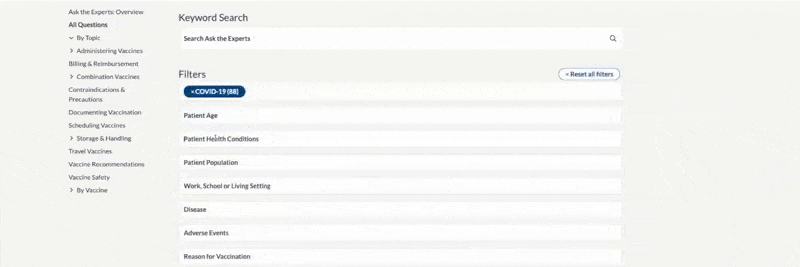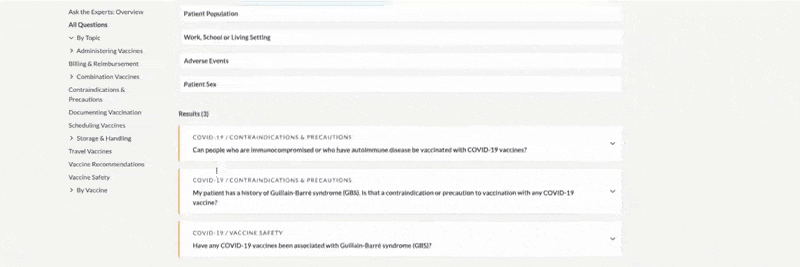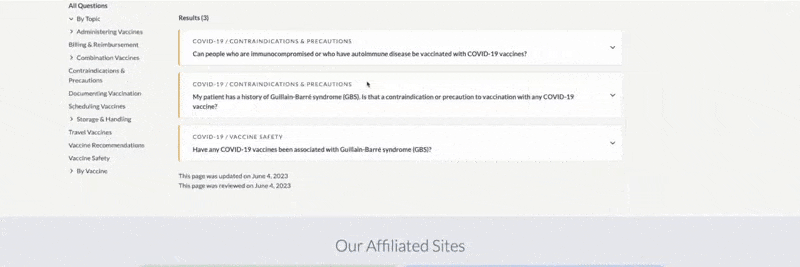
  • Filters are easily added and removed. Click or tap on the X to remove individual filters or choose “Reset All Filters” to remove all filters.
Results (1409)

CDC publishes and routinely updates a comprehensive Vaccine Storage and Handling Toolkit covering topics such as vaccine storage units, temperature monitoring devices, and inventory management, vaccine transport and emergency vaccine storage and handling. The toolkit also contains troubleshooting guides to assist with vaccine storage unit issues or temperature excursions. A separate addendum addresses issues specific to the storage and handling of mpox vaccine. This resource, along with other vaccine storage and handling resources from CDC, is available online at www.cdc.gov/vaccines/hcp/storage-handling/.

In addition, Immunize.org maintains many free, downloadable materials at www.immunize.org/clinical/topic/storage-handling/.

Last reviewed: April 10, 2026

For routine vaccination, children without contraindications to MMR vaccine should receive 2 doses of MMR vaccine with the first dose at age 12–15 months old and the second dose at age 4–6 years old, usually given before kindergarten entry. The minimum interval is 28 days for dose 2. If you have an outbreak in your community or a child is traveling internationally, then consider using the minimum interval instead of waiting until age 4–6 years old for dose 2.

Last reviewed: August 10, 2026

Commercially available laboratory tests for varicella antibody are usually based on a technique called EIA (enzyme immunoassay). Though these tests are sufficiently sensitive to detect antibody resulting from varicella zoster virus infection, they are generally not sensitive enough to detect vaccine-induced antibody. The more sensitive assays needed to detect vaccine-induced antibody are not widely available. This is why CDC does not recommend antibody testing after varicella vaccination.

Last reviewed: August 12, 2026

Immunocompromised adults age 19 years and older without evidence of exposure to live varicella virus through a history of chickenpox, zoster, or documentation of vaccination with live varicella vaccine (Varivax or ProQuad, Merck) or the historically available zoster vaccine live (Zostavax, Merck) should be evaluated further for their risk of zoster before receiving Shingrix recombinant zoster vaccine. Birth before 1980 is not sufficient proof of a history of primary varicella infection (chickenpox) for immunocompromised adults.

Vaccination with varicella vaccine to prevent chickenpox may be considered for a patient with well-controlled HIV (e.g., CD4+ T-lymphocyte percentage of at least 15% and a count of at least 200 cells per microliter) and no evidence of a history of varicella disease or vaccination. Vaccination may be considered for a patient who has a CD4 count of at least 200 cells per microliter but no information on percentage. Vaccination is contraindicated if a patient has laboratory information on the CD4 percentage and/or count and either measure falls below the recommended acceptable threshold for vaccination.

For other situations involving immunocompromised adults with no evidence of a history of varicella disease or vaccination, see detailed guidance provided by CDC at www.cdc.gov/shingles/hcp/vaccine-considerations/immunocompromised-adults.html.

Last reviewed: August 12, 2026

Yes. Doses of FluMist administered in past seasons can be counted.

Last reviewed: October 11, 2026

The answer is no. The American Academy of Pediatrics and CDC recommend only a single dose of RSV preventive antibody product for infants younger than 8 months of age, administered during, or just before, RSV season. An infant who receives nirsevimab at the end of one season and who is younger than age 8 months at the beginning of the next season should not be given an additional dose of either RSV preventive antibody product. Likewise, children younger than 8 months of age born near the end of the previous RSV season to mothers who received an effective dose of Abrysvo RSV vaccine during pregnancy are NOT recommended to receive an RSV preventive antibody product at the beginning of the next season. 

Children who meet the high-risk criteria to receive a dose of nirsevimab to protect them through their second RSV season should be at least 8 months of age (and younger than 20 months of age) at the time of administration of the second-season nirsevimab dose.

Last reviewed: September 23, 2026


1:51

View All Video Questions

Last reviewed: June 26, 2026

A dose of MMR vaccine administered up to 4 days before the first birthday may be counted as valid. However, school entry requirements in some states may mandate administration on or after the first birthday. The 4-day “grace period” also may be applied to the 28-day minimum interval between two doses of MMR if the interval is inadvertently shorter than 28 days, although you should never plan to administer the second dose earlier than the 28-day minimum interval. This 4-day “grace period” does not apply to the strict 28-day minimum interval between two different live vaccines (e.g., MMR and varicella vaccines), if not administered at the same visit.

Last reviewed: August 10, 2026

Although not at increased risk for hepatitis A virus (HAV) infection, people with chronic liver disease are at increased risk for fulminant hepatitis A, hospitalization, and death if they become infected with HAV. For this reason, HepA vaccination is recommended for them.

Last reviewed: June 25, 2023

No, Dengvaxia is not included in the VICP at this time.

For additional information, visit www.hrsa.gov/vaccine-compensation/faq.

Last reviewed: January 17, 2025

You should use separate alcohol wipes to clean the vial top and the patient’s skin.

Last reviewed: February 27, 2025

Inactivated vaccines can be administered to people who take immunosuppressive drugs or who have a condition that causes them to be immunocompromised. The vaccines might not be as effective as they would be when given to a person with an intact immune system. If possible, the immunosuppressive drug should be discontinued for a month prior to vaccination, then allow the vaccine 2–3 weeks to generate an immune response before restarting the immunosuppressive treatment, but obviously, this is not always possible.

Determination of altered immunocompetence is important because incidence or severity of some vaccine-preventable diseases is greater in people with altered immunocompetence. As a result, certain vaccines (e.g., inactivated influenza vaccine and pneumococcal vaccines) are recommended specifically for people with altered immunocompetence.

More information can be found in ACIP’s “General Best Practices Guidelines for Immunization” available at www.cdc.gov/vaccines/hcp/imz-best-practices/altered-immunocompetence.html.

Last reviewed: August 29, 2022

Yes. All adolescents should receive one dose of Tdap vaccine to protect them from pertussis, even if they have already received Td. It is important to do this right away (no minimal interval is required), especially if they are in contact with an infant younger than age 12 months, work in a healthcare setting where they have direct contact with patients, or live in a community where pertussis is occurring.

Last reviewed: March 31, 2022

Few data are available on the effect of MenB vaccines on pregnancy. The manufacturers do not consider pregnancy to be a contraindication to use of MenB. GSK has established a Vaccination in Pregnancy registry. People who receive Bexsero during pregnancy may access information about the GSK Bexsero Pregnancy Registry here: https://pregnancyregistry.gsk.com/bexsero.html. Pfizer also maintains a Vaccination in Pregnancy registry for Trumenba, although specific contact details for this registry are not available. In general, vaccination against MenB should be deferred during pregnancy; however, MenB may be administered if, in the judgment of the clinician, the benefits outweigh any potential risk.

Last reviewed: November 15, 2024

Yes. If an HPV vaccine dose is administered at less than the recommended minimum interval, then the dose should be repeated. The repeat third dose should be repeated 5 months after the first dose or 12 weeks after the invalid third dose, whichever is later.

Last reviewed: March 2, 2024

Twinrix is licensed as a 3-dose series for people age 18 years and older (minimum interval between dose 1 and dose 2 is 4 weeks; minimum interval between dose 2 and dose 3 is 5 months). It is also approved for use in an accelerated 4-dose schedule in adults, with doses given at 0, 7, and 21-30 days, followed by a booster dose at 12 months. There is no accelerated schedule for single antigen HepA or HepB vaccines, so the recommendations below presume the use of the Twinrix 3-dose routine schedule, with a minimum interval between dose 1 and dose 2 of 4 weeks.

If Twinrix is not available or if you choose not to use Twinrix to complete the hepatitis A (HepA) and hepatitis B (HepB) series, you should do the following:

  • If 1 dose of Twinrix was given, complete the series with 2 adult doses of HepA and 2 adult doses of HepB.
  • If 2 doses of Twinrix were given, complete the schedule with 1 adult dose of HepA and 1 adult dose of HepB.

Another way to consider this is as follows:

  • A dose of Twinrix contains a standard adult dose of HepB and a pediatric dose of HepA. So, a dose of Twinrix can be substituted for any dose of the HepB series but not for any dose of the HepA series.
  • Any combination of 3 doses of adult HepB or 3 doses of Twinrix is a complete series of HepB vaccine
  • One dose of Twinrix and 2 doses of adult HepA is a complete series of HepA
  • Two doses of Twinrix and 1 dose of adult HepA is a complete series of HepA
Last reviewed: January 17, 2025

No. If there is no longer a CSF leak, pneumococcal conjugate vaccine is not recommended, unless there is another risk factor for invasive pneumococcal disease or an age-based indication.

Last reviewed: November 13, 2024

Screening may be done with the hepatitis B surface antigen (HBsAg) test only. This blood test will tell whether a mother has current HBV infection that can be transmitted to the infant. Ordering a total antibody to hepatitis B core antigen (total anti-HBc) and/or anti-HBs are not useful when screening to prevent perinatal HBV infections and should not be included in screening during pregnancy for risk of perinatal HBV infection. Total anti-HBc will be positive in all HBsAg-positive people and anti-HBs is rarely positive in an HBsAg-positive person. Pregnant people who are found to be positive should be tested for HBV DNA to guide the use of maternal antiviral therapy during pregnancy for the prevention of perinatal HPV transmission (see MMWR 2018;67 [RR-1]:13).

An infant born to a mother for whom HBsAg screening test results during pregnancy are not available but other evidence suggesting maternal HBV infection exists (e.g., presence of HBV DNA, HBeAg-positive, or mother known to be chronically infected with HBV) should be managed as if born to an HBsAg-positive mother. The infant should receive both HepB and HBIG within 12 hours of birth. The mother should also be referred to their jurisdiction’s Perinatal Hepatitis B Prevention Program for case management to ensure that the infant receives timely prophylaxis and follow-up.

Last reviewed: January 17, 2025

Valacyclovir, acyclovir, and famciclovir are antiviral medications that are active against herpesviruses, including varicella zoster virus. The risk of shingles risk is reduced during antiviral treatment. Since Shingrix is not a live virus vaccine, Shingrix may be administered while patients are taking antiviral medications if indicated.

A patient who is taking a prophylactic antiviral for a fixed period of time while their immune system recovers from HCT, should ideally initiate vaccination with Shingrix about 2 months before discontinuing antiviral therapy.

Regardless of the duration of antiviral therapy after HCT, CDC recommends that autologous HCT recipients wait at least 3 months after transplant before initiating Shingrix vaccination. Allogenic HCT recipients should wait at least 6 months after transplantation. For additional details on timing after HCT, see www.cdc.gov/shingles/hcp/vaccine-considerations/immunocompromised-adults.html.

Last reviewed: August 25, 2025

The optimal timing for nirsevimab (Beyfortus, Sanofi) or clesrovimab (Enflonsia, Merck) to be administered is shortly before the RSV season begins; however, these products may be administered to eligible infants and children at any time during the season.

The time to administer RSV preventive antibody products is during the months of October through March in most areas in the United States, unless otherwise advised by state or territorial public health authorities. Adjustment of timing due to RSV activity outside this typical timeframe is most likely to be necessary in tropical or sub-tropical climates and in Alaska.

Last reviewed: August 24, 2025

The CDC Storage and Handling Toolkit, available at www.cdc.gov/vaccines/hcp/downloads/storage-handling-toolkit.pdf, contains information about recommended features to look for when selecting a temperature monitoring device or storage unit. If you store Vaccines for Children (VFC) or other federally-purchased vaccines, you may contact your state immunization manager or Vaccines for Children (VFC) coordinator for additional information on their recommendations or requirements. Contact information can be found here: www.immunizationmanagers.org/about-aim/program-manager-directory/.

A good option is to look for units that have the NSF/ANSI 456 certification. A refrigerator or freezer that is NSF-certified for vaccine storage means the units have been tested and certified to meet the NSF/American National Standards Institute (ANSI) 456 standards for construction and performance of vaccine refrigerators and freezers used in healthcare settings where vaccines are given. These standards were developed through a collaboration with NSF, CDC, healthcare providers, public health agencies, equipment manufacturers, and vaccine manufacturers, including experts from Immunize.org.

CDC does not require NSF-certified units for vaccine storage in the Vaccines for Children program or any other federal program. Not all storage units capable of reliably storing vaccines have this certification; however, all storage unit models with this certification have met design and performance standards to properly store vaccines under a range of normal clinic conditions.

Last reviewed: April 10, 2026

If you cannot verify a healthcare employee’s history of chickenpox, the employee should receive 2 doses of varicella vaccine at least 4 weeks apart. For details, refer to pages 16 and 26 of the 2007 CDC recommendations Prevention of Varicella at www.cdc.gov/mmwr/pdf/rr/rr5604.pdf.

Last reviewed: August 12, 2026

Pregnant women have historically been at an increased risk of severe disease, adverse pregnancy outcomes, and maternal death from COVID-19 infections. Studies have shown that antibodies produced after COVID-19 vaccination during pregnancy are transferred to the newborn, and COVID-19 vaccination during pregnancy reduces the risk of COVID-19 hospitalization in infants younger than 6 months.

CDC’s September 2026 clinical considerations have removed text documenting the safety and benefits of COVID-19 vaccination during pregnancy; however, CDC continues to routinely recommend COVID-19 vaccination for all adults, including during pregnancy, and pregnancy is a high-risk condition for severe COVID-19.

The American College of Obstetricians and Gynecologists (ACOG) routinely recommends all pregnant women receive any age-appropriate 2026–2027 COVID-19 vaccine if they have not already received one. ACOG recommends vaccination in any trimester as soon as possible when a dose is due. ACOG’s guidance does not call for an extra dose solely because a person becomes pregnant after receiving the current-season dose. Current ACOG recommendations are available here: www.acog.org/clinical/clinical-guidance/practice-advisory/articles/2020/12/covid-19-vaccination-considerations-for-obstetric-gynecologic-care. ACOG’s 2026 maternal schedule is available at www.acog.org/clinical-information/maternal-immunization-schedule.

Last reviewed: October 18, 2026


2:15

View All Video Questions

Last reviewed: January 9, 2026


1:34

View All Video Questions

Last reviewed: January 9, 2026

Yes. However, if two parenteral or intranasal live vaccines (MMR, varicella, LAIV and/or yellow fever) are not administered on the same day, they should be separated by an interval of at least 28 days.

Last reviewed: August 10, 2026

Yes. Mothers who have received HepB should still be screened for HBsAg early in each pregnancy. Just because a pregnant person has been vaccinated does not mean they are HBsAg negative. Since postvaccination testing is not performed for most vaccinated people, the mother could have been vaccinated when already actively infected.

Last reviewed: January 17, 2025

In published reports of three serologic surveys conducted among United States wastewater workers and appropriate comparison populations, no substantial or consistent increase in the prevalence of anti-HAV was identified among wastewater workers. No work-related instances of hepatitis A transmission have been reported among wastewater workers in the United States. In addition, in the United States, outbreaks of hepatitis A caused by flooding, which can carry raw sewage, have not been reported.

Last reviewed: June 25, 2023

No. Twinrix contains 50% less hepatitis A antigen component than Havrix, GSK’s monovalent HepA vaccine [720 vs. 1440 EL.U.], so the patient would not receive the recommended dose of HepA vaccine antigen.

Last reviewed: January 27, 2025

No. You should only use the (0.4% NaCl) diluent provided with the Dengvaxia vaccine vial. Contact your immunization program or the manufacturer for additional guidance.

Last reviewed: January 17, 2025

Yes. There is no need to observe any minimum interval between doses of Td and Tdap except when administered as part of a catch-up primary series of tetanus vaccine.

Last reviewed: March 31, 2022

No. Beta thalassemia minor is a hemoglobinopathy, but compared to sickle cell disease, these patients have less risk for functional asplenia, and therefore do not have a significantly increased risk of invasive pneumococcal disease.

Last reviewed: November 13, 2024

The stopper of a single-dose vial (SDV) is often assumed to be sterile. However, not all vaccine manufacturers guarantee the tops of unused vials are sterile, and the manner in which the cover over the stopper is removed can potentially contaminate the stopper. Therefore, using friction and a sterile alcohol pad to swab the stopper may help to assure aseptic technique in preparing the SDV prior to inserting a sterile syringe. Alcohol evaporates quickly and will dry while the needle is being prepared for insertion into the vial.

Last reviewed: February 27, 2025

The risk for zoster and its severe morbidity and mortality is much greater for immunosuppressed people. A 2-dose series of Shingrix recombinant zoster vaccine should be administered as soon as possible while the person’s immune system is intact. In cases such as this, depending upon the timing of chemotherapy initiation, you may wish to consider a shorter interval of at least 4 weeks (1 month) in order to complete the series as soon as possible.

Last reviewed: August 25, 2025

Some American Indian or Alaska Native (AI/AN) children experience higher rates of severe RSV disease than the general population. A recent study found that the incidence of hospitalization due to RSV among some AI/AN children in their second year of life was four to ten times higher than that of similar-aged children in multiple study sites in the United States. Also, some AI/AN communities live in remote regions, making transportation of children with severe RSV to obtain medical care more challenging. Although the available data are limited and may not apply to all AI/AN children in all settings, ACIP recommends nirsevimab (Beyfortus, Sanofi) for AI/AN children entering their second RSV season.

The American Academy of Pediatrics (AAP) explains its recommendation for AI/AN children in its August 2025 policy statement (https://doi.org/10.1542/peds.2025-073923) as follows:

American Indian and Alaska Native Children are included in the high-risk category, because they experience significantly higher rates of severe RSV disease and hospitalization, with children living in rural and reservation communities most impacted. Evidence supports that this increased risk is associated with social drivers of health, with specific attention to running water access, transportation difficulties, household crowding, and indoor air quality.

Last reviewed: August 24, 2025

No. Documented receipt of 2 doses of varicella vaccine supersedes results of subsequent serologic testing. Most commercially available tests for varicella antibody are not sensitive enough to detect vaccine-induced antibody, which is why CDC does not recommend post-vaccination testing. For more information, see page 24 of ACIP’s Immunization of Health-Care Personnel, published November 25, 2011, and available at www.cdc.gov/mmwr/pdf/rr/rr6007.pdf.

Last reviewed: August 12, 2026

The two doses may be the same or different products.

Last reviewed: October 11, 2026

Yes. The American College of Obstetricians and Gynecologists (ACOG) recommends COVID-19 vaccination for eligible lactating and postpartum patients. Breastfeeding does not need to be interrupted for vaccination. See www.acog.org/clinical-information/maternal-immunization-schedule.

Last reviewed: October 18, 2026


1:38

View All Video Questions

Last reviewed: August 24, 2025

Yes. Adolescents and adults who started the HPV vaccine series prior to the 15th birthday and who are not immunocompromised are considered to be adequately vaccinated with just one additional dose of HPV vaccine.

Last reviewed: March 2, 2024

People with clotting factor disorders were originally recommended to receive hepatitis A vaccine (HepA) in 1996. At that time, the process used to make clotting factor supplements did not reliably inactivate hepatitis A viruses and recipients of these products had an increased risk of hepatitis A virus (HAV) infection. Modern blood donor screening and virus reduction steps have drastically reduced that risk. In addition, more than 80% of people with clotting factor disorders now receive recombinant clotting factor concentrates that are sterilized and have no risk of HAV transmission. As a result of these factors, people with clotting factor disorders now have no greater risk of hepatitis A than the general population and are no longer recommended to receive HepA vaccine unless it is otherwise indicated.

Last reviewed: June 25, 2023

The earlier the evaluation is done, the better. Consultation with or referral to a liver disease specialist (such as a hepatologist, gastroenterologist, or infectious disease specialist) should be done. The consulting/referral physician should be aware of the patient’s obstetrical status. In addition, the patient’s sex partner and children or other household contacts should be tested for HBV infection (total anti-HBc and HBsAg) as soon as possible. If any are susceptible to HBV infection (total anti-HBc and HBsAg negative), they should be vaccinated. If any are HBsAg positive, they should be referred to or have consultation with a liver disease specialist.

Last reviewed: January 17, 2025

Using a pre-packaged sterile alcohol prep pad is recommended to maintain aseptic technique. Not only are cotton balls not sterile, but neither is a bottle of sterile alcohol, once it’s opened.

Last reviewed: February 27, 2025

Store both the vaccine antigen and the diluent in a refrigerator at 36°F–46°F (2°C–8°C). Do not freeze. Protect from light. After reconstitution, administer Dengvaxia immediately or store refrigerated at 36°F–46°F (2°C–8°C) and use within 30 minutes.

Do not use the vaccine if it has been reconstituted for over 30 minutes. Contact your public health immunization program or the manufacturer for advice if vaccination occurs using vaccine that has been reconstituted more than 30 minutes, or in the event of other storage or handling errors.

The manufacturer package insert contains additional information and can be found at www.fda.gov/media/124379/download.

For complete information on vaccine storage and handling best practices and recommendations, please refer to CDC’s Vaccine Storage and Handling Toolkit at www.cdc.gov/vaccines/hcp/admin/storage/toolkit/storage-handling-toolkit.pdf.

Last reviewed: January 17, 2025

You should use DTaP to catch up children younger than age 7 years. In addition, ACIP recommends giving one dose of Tdap to children age 7–10 years who were not fully vaccinated against pertussis before their seventh birthday. Children age 7–10 who require more than one dose of tetanus-containing vaccine to be up to date with diphtheria or tetanus immunization may be given either Td or Tdap for doses needed after the initial Tdap dose. Although this is an off-label use of the vaccines, it’s important that you vaccinate these unvaccinated or undervaccinated older children with Tdap as well as any other adolescent or adult who hasn’t received Tdap previously.

Last reviewed: May 30, 2024

Adults that received PCV13 should complete the pneumococcal series with PCV20 or PCV21 vaccination at least 1 year after PCV13. PCV15 and PPSV23 are not recommended in this situation.

Last reviewed: November 13, 2024

There is no specific indication for meningococcal vaccine in this patient. Risk–based recommendations are restricted to specific forms of altered immunocompetence (persistent complement component deficiency, functional or anatomic asplenia, use of complement inhibitors such as eculizumab [Soliris], ravulizumab [Ultomiris] or sutimlimab [Enjaymo], and HIV infection) and do not include other forms of altered immunocompetence.

Last reviewed: November 15, 2024

A person who was on immunosuppressive chemotherapy in the past but is not expected to be immunocompromised again may follow routine recommendations for shingles vaccination at age 50 years or older. If the patient is age 19 or older and expected to require repeated exposure to immunosuppressive chemotherapy in the future, then it is preferable to vaccinate now while the patient’s immune system is more robust.

Last reviewed: August 25, 2025

Palivizumab (Synagis, AstraZeneca) is a short-acting monoclonal antibody product that is administered monthly. Synagis is no longer recommended for use by the American Academy of Pediatrics (AAP). The manufacturer is discontinuing the product in December 2025.

Last reviewed: August 24, 2025

ProQuad was licensed in 2005 for use in children ages 12 months through 12 years. It combines the measles-mumps-rubella (MMR) and varicella vaccines and therefore can be used in place of the individual MMR and varicella vaccines given at ages 12–15 months and 4–6 years. Because of an increased risk of febrile seizures when MMRV is administered as a first dose to children 12-23 months of age, the American Academy of Pediatrics (AAP) recommends that providers considering using MMRV in this age group should discuss the benefits and risks of vaccination options with parents or caregivers, and use MMRV in this situation when the informed parent or caregiver prefers this option. CDC recommends separate MMR and varicella vaccination for eligible children younger than age 4 years, unless the parent prefers MMRV. For more information, consult the package insert at www.merck.com/product/usa/pi_circulars/p/proquad/proquad_pi_4171.pdf.

Last reviewed: August 12, 2026

The second dose of MMR may be given as early as 28 days after the first dose, and be counted as a valid dose, if both doses were given after the first birthday. The second dose is not a booster, but rather it is intended to produce immunity in the small number of people who fail to respond to the first dose. The risk of measles is higher in school-age children than those of preschool age, so it is important to receive the second dose by school entry. It is also convenient to give the second dose at this age, since the child will have an immunization visit for other school entry vaccines.

Last reviewed: August 10, 2026

The recommended minimum interval between two doses of varicella vaccine for children 12 months through 12 years of age is 12 weeks. However, the second dose of varicella vaccine does not need to be repeated if records show it was separated from the first dose by at least 4 weeks. See www.cdc.gov/vaccines/hcp/imz-best-practices/timing-spacing-immunobiologics.html, Table 3-2.

Last reviewed: August 12, 2026

The IDSA guidelines indicate that persons receiving rituximab should be considered to have high-level immunosuppression. Both inactivated and live vaccines should be withheld at least 6 months following treatment with lymphocyte depleting medications such as rituximab. As for the IG, the interval to live vaccination depends on the dose. For guidance, please refer to the Timing and Spacing of Immunobiologics section of CDC’s General Best Practices for Immunization, Table 3-6: “Recommended intervals between administration of antibody-containing products and measles- or varicella-containing vaccine, by product and indication for vaccination” at www.cdc.gov/vaccines/hcp/imz-best-practices/timing-spacing-immunobiologics.html. This interval could be as long as 11 months, depending on the dose he receives.

Last reviewed: August 12, 2026

The child should receive the dose appropriate for the child’s age at the time of the visit. At age 37 months, give a 0.5 mL dose of Fluzone.

Last reviewed: October 11, 2026

IDSA strongly recommends age-appropriate 2026–2027 COVID-19 vaccination for immunocompromised adults and children, with timing tailored to the condition and treatment. Details of timing considerations are provided in Table 1 of the IDSA recommendations at: www.idsociety.org/practice-guideline/Seasonal-RTI-Vaccinations-in-Immunocompromised-Patients/. For children and adolescents through age 18 years, use AAP’s 2026 immunization schedule: www.aap.org/ImmunizationSchedule. CDC provides detailed schedule tables here: www.cdc.gov/covid/hcp/vaccine-considerations/immunocompromised.html.

Immunize.org also provides current COVID-19 vaccination resources and standing orders templates on its main page: www.immunize.org/vaccines/a-z/covid-19/. The following links provide standing orders templates:

Due to the timing and clinical considerations outlined by IDSA, the standing orders templates refer moderately or severely immunocompromised patients for individual clinical evaluation rather than providing their complete dosing schedule. Use the AAP or CDC schedules linked above for dosing schedules.

CDC recommends that people who are moderately or severely immunocompromised and previously unvaccinated receive a 2-dose (protein subunit) or 3-dose (mRNA) initial series of COVID-19 vaccine, with an additional dose 6 months later of any age-appropriate COVID-19 brand (minimum interval of 2 months for Nuvaxovid, Spikevax, or Comirnaty; 3-month minimum interval for mNexspike). CDC recommends use of the same manufacturer for all doses of the initial series when feasible. Spikevax and mNexspike are both made by Moderna and are interchangeable in ages 12 years and older. These recommendations were originally made in the 2023–24 season and are endorsed by IDSA.

CDC recommends that those who completed an initial series before the 2026–2027 vaccines were available receive 2 doses of 2026–2027 COVID-19 vaccine (any age-appropriate brand) about 6 months apart (minimum interval of 2 months for Nuvaxovid, Spikevax, or Comirnaty; 3-month minimum interval for mNexspike).

IDSA recommends a single dose of current season vaccine and remarks that a second dose 6 months later may extend protection, but it does not routinely recommend a second dose.

AAP’s 2026 schedule permits additional doses for moderately or severely immunocompromised children and adolescents based on shared clinical decision-making, at least 2 months after the most recent dose. For ages 12 through 18 years, AAP lists a 2-month minimum interval for the post-initial-series dose, including either Moderna product; CDC specifically recommends a 3-month interval when using mNexspike.
Last reviewed: October 18, 2026

ACIP recommends that children who travel or live abroad should be vaccinated at an earlier age than that recommended for children who reside in the United States. Before their departure from the United States, children age 6 through 11 months should receive 1 dose of MMR. The risk for measles exposure can be high in high-, middle- and low-income countries. Consequently, CDC encourages all international travelers to be up to date on their immunizations regardless of their travel destination and to keep a copy of their immunization records with them as they travel. For additional information on the worldwide measles situation, and on CDC’s measles vaccination information for travelers, go to wwwnc.cdc.gov/travel.

Last reviewed: August 10, 2026
  • Infants born to mothers for whom HBsAg testing results during pregnancy are not available but other evidence suggestive of maternal HBV infection exists (for example presence of HBV DNA, HBeAg-positive, or mother known to be chronically infected with HBV) should be managed as if born to an HBsAg-positive mother.
  • Mothers admitted for delivery without documentation of HBsAg test results should have blood drawn and tested as soon as possible after admission.
  • While test results are pending, all infants with birth weights of 2,000 grams or more born to mothers without documentation of HBsAg test results should receive the first dose of single-antigen HepB (without HBIG) within 12 hours of birth. Only single antigen HepB vaccine should be used for the birth dose.
  • If the mother is determined to be HBsAg positive, the infant should receive HBIG as soon as possible but no later than age 7 days, and the vaccine series should be completed according to a recommended schedule for infants born to HBsAg-positive mothers.
  • If the mother is determined to be HBsAg negative, the vaccine series should be completed according to a recommended schedule for infants born to HBsAg-negative mothers.
Last reviewed: January 17, 2025

Although second-hand smoke and other environmental conditions have been identified as risk factors for meningococcal disease, ACIP does not include them as indications for MenACWY vaccination. Providers may always use their clinical judgment in situations not addressed by ACIP.

Last reviewed: November 15, 2024

People who have received 2 doses of HPV vaccine separated by less than 5 months should receive a third dose 6–12 months after dose #1 and at least 12 weeks after dose #2, regardless of their age at the time of the first dose. The recommended interval for the second dose in the 2-dose schedule (indicated when the first dose is given before age 15) is 6 months and the minimum interval is 5 months.

Last reviewed: March 2, 2024

This child needs to complete the primary series with 1 dose of Td or Tdap, administered no earlier than 6 months after the Tdap dose given at age 11 years. After that, the child needs a booster dose of Td or Tdap every 10 years. An easy way to determine how to catch up a child is to consult “Recommended Immunization Schedules for Persons Aged 0 Through 18 Years, U.S.” The schedule is approved by CDC, AAP, and AAFP and is released early in each calendar year. It includes a catch-up schedule for children who have fallen behind (see www.cdc.gov/vaccines/hcp/imz-schedules/index.html).

Last reviewed: August 23, 2024

What you describe is a good strategy for administration of the 2-dose pneumococcal vaccine series of PCV15 and PPSV23 to people age 50 years and older if you prefer not to complete their PCV vaccination with a single dose of either PCV20 or PCV21. ACIP does not define “one year” but this is assumed to be one calendar year. Receiving PPSV23 a few days or weeks earlier than one calendar year after PCV15 is not a medical problem. However, it could be a problem for reimbursement since Medicare will only pay for both a PCV15 vaccine and a PPSV23 vaccine if they are given at least 11 months apart. Private insurance may have similar rules. Here is the wording from the Centers for Medicare and Medicaid (CMS): “An initial pneumococcal vaccine may be administered to all Medicare beneficiaries who have never received a pneumococcal vaccine under Medicare Part B. A different, second pneumococcal vaccine may be administered 1 year after the first vaccine was administered (i.e., 11 full months have passed following the month in which the last pneumococcal vaccine was administered).”

Last reviewed: November 13, 2024

In general, the entire volume should be used even if it is a little more than 0.5 mL. Discarding the excess vaccine is not required or recommended.

An exception to this general rule is the presentation of recombinant zoster vaccine (Shingrix, GSK) that requires reconstitution. The Shingrix adjuvant solution vial may contain up to 0.75 mL of liquid. The entire volume of the adjuvant solution should be withdrawn and used to reconstitute the lyophilized vaccine. After mixing, withdraw the recommended dose of 0.5 mL. Any reconstituted Shingrix vaccine left in the vial should be discarded.

Last reviewed: August 25, 2025

Hepatitis C infection is not a contraindication for Shingrix recombinant zoster vaccination. However, if someone with hepatitis C is receiving a medication that can cause immunosuppression, they should consult with their healthcare provider to discuss the clinical considerations for the timing of vaccination. Detailed guidance is available at www.cdc.gov/shingles/hcp/vaccine-considerations/immunocompromised-adults.html.

Last reviewed: August 25, 2025

If you are unable to obtain prenatal records or verify receipt of maternal RSV vaccine, CDC recommends that the baby receive nirsevimab (Beyfortus, Sanofi) or clesrovimab (Enflonsia, Merck), particularly if it is shortly before or during the RSV season. Don’t forget to check the state immunization information system (IIS) for the mother’s vaccination record. RSV vaccination during a previous pregnancy does not protect through later pregnancies. If the mother received RSV vaccine during a previous pregnancy, nirsevimab or clesrovimab is indicated for this infant. It is also important to attempt to verify from the birthing facility records whether this baby received an RSV preventive antibody product prior to discharge to avoid giving an unnecessary second dose.

Last reviewed: August 24, 2025

Post-licensure studies of MMRV suggested that, during the 5–12 days after vaccination, approximately one additional febrile seizure occurred among every 2,600 children ages 12 through 23 months vaccinated with a first dose of MMRV vaccine compared with children in the same age group vaccinated with separate first doses of MMR vaccine and varicella vaccine administered during a single office visit.

For this reason, the recommendations for use of MMRV vaccine are as follows:

  • The routinely recommended ages for measles, mumps, rubella, and varicella vaccination are age 12 through 15 months for the first dose and age 4 through 6 years for the second dose.
  • The American Academy of Pediatrics (AAP) advises that for the first dose of measles, mumps, rubella, and varicella vaccines at age 12 through 23 months, providers may use either MMR vaccine and varicella vaccine or MMRV vaccine. Providers who are considering administering MMRV vaccine should discuss the benefits and risks of both vaccination options with the parents or caregivers. Unless the parent or caregiver expresses a preference for MMRV vaccine, CDC recommends that providers administer separate MMR vaccine and varicella vaccine for the first dose in eligible children younger than age 4 years.
  • AAP recommends that MMRV is generally preferred for the second dose typically administered at age 4 through 6 years to reduce the number of injections needed. Historically, CDC has also stated that for the second dose of measles, mumps, rubella, and varicella vaccines at any age (15 months through 12 years) and for the first dose, if given at age 48 months and older, use of MMRV vaccine generally is preferred, if available, over separate injections of its equivalent component vaccines to reduce the number of injections (i.e., MMR vaccine and varicella vaccine).
  • A personal or family (e.g., sibling or parent) history of seizures of any etiology (i.e., cause) is a precaution for MMRV vaccination, and such children generally should be vaccinated with MMR vaccine and varicella vaccine.

The complete original recommendations for the use of MMRV vaccine by ACIP in 2010 are available on CDC’s website at www.cdc.gov/mmwr/pdf/rr/rr5903.pdf.

The current AAP childhood immunization schedule is available on the Immunize.org website at: www.immunize.org/official-guidance/hpo/rec-schedules/.

Last reviewed: August 12, 2026

This page was updated on .